
The New Weight-Loss Conversation
Why the conversation around obesity is moving beyond diets, willpower and the weighing scale — towards metabolism, health and individually appropriate treatment.

For years, the conversation around weight followed a familiar script: eat less, exercise more, be disciplined — and if the weight returned, try harder.
But the vocabulary of modern obesity care is becoming considerably broader. Clinicians may now discuss metabolism, diabetes, fatty liver, sleep apnea, hormonal health, hunger regulation, medications, non-surgical interventions, bariatric surgery and robotic-assisted surgical technology.
The shift matters because obesity is not simply an appearance issue. For some people, increasing weight exists alongside metabolic disease, disturbed sleep, reduced mobility, breathlessness, joint burden or repeated cycles of weight loss and regain.
That changes the question from “How do I lose weight?” to something more useful: “What is happening to my health, and what options should I understand?”
When weight becomes more than weight
The turning point is often ordinary. A flight of stairs feels harder. An ultrasound mentions fatty liver. Blood sugar rises. Sleep becomes disrupted. Knees begin to complain. Daily movement requires more effort.
At that stage, weight is no longer only a number or a clothing size. It becomes part of a larger health conversation.
Lifestyle remains important, but modern obesity care increasingly recognises that sustained weight management can be influenced by biological, metabolic, behavioural and medical factors — not simply motivation.
Obesity has spent too long inside a morality story. Medicine asks a different question.A shift from judgement toward health
The problem with “just eat less”
People living with obesity are often surrounded by advice before they ever enter a clinic. Eat less. Avoid carbohydrates. Walk more. Join a gym. Be stronger.
Yet repeated dieting and weight regain are familiar experiences for many people seeking obesity care. Appetite, satiety, medications, metabolic conditions, sleep, activity, eating patterns and previous weight-loss history can all become relevant during a clinical discussion.
This does not mean lifestyle behaviour is irrelevant. It means effective medical care should avoid reducing a complex condition to a character judgement.


The question is not simply: “Which treatment loses the most weight?”
In contemporary obesity care, different patients can require very different conversations.
BMI may be relevant, but so are medical history, obesity-associated health conditions, previous attempts at weight management, current medications, eating behaviour and broader health goals.
At Mohak Bariatrics & Robotics, the discussion may involve medical, non-surgical or surgical weight-management pathways. The appropriate approach depends on clinical evaluation rather than a one-treatment-fits-all model.
The modern weight-management spectrum
Today's patient may encounter several different categories of obesity care. More options, however, do not mean every option is appropriate for every person.
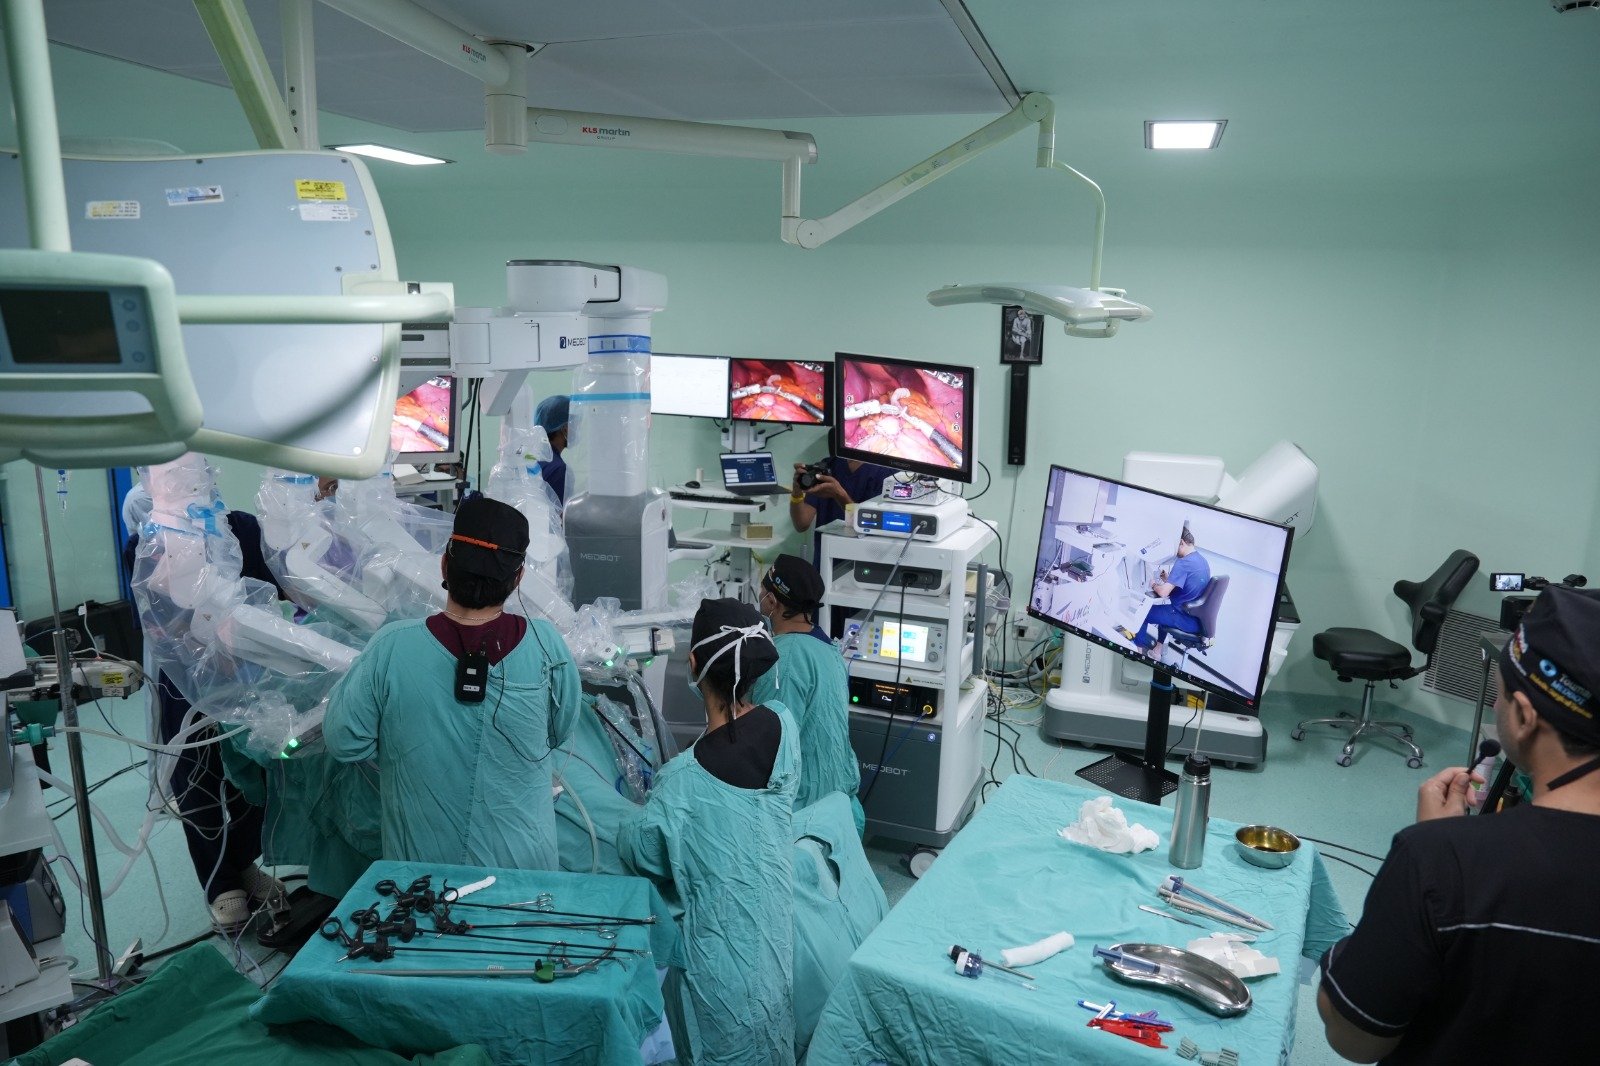
Surgery changed. So did the technology around it.
Robotic-assisted surgery is sometimes described in futuristic language, but the most important distinction is straightforward: the robotic system remains under the surgeon's control.
Depending on the procedure and robotic platform, the technology may support visualisation, instrument articulation, ergonomics and operative execution. It does not replace clinical judgement, patient assessment, surgical planning or the operating team.

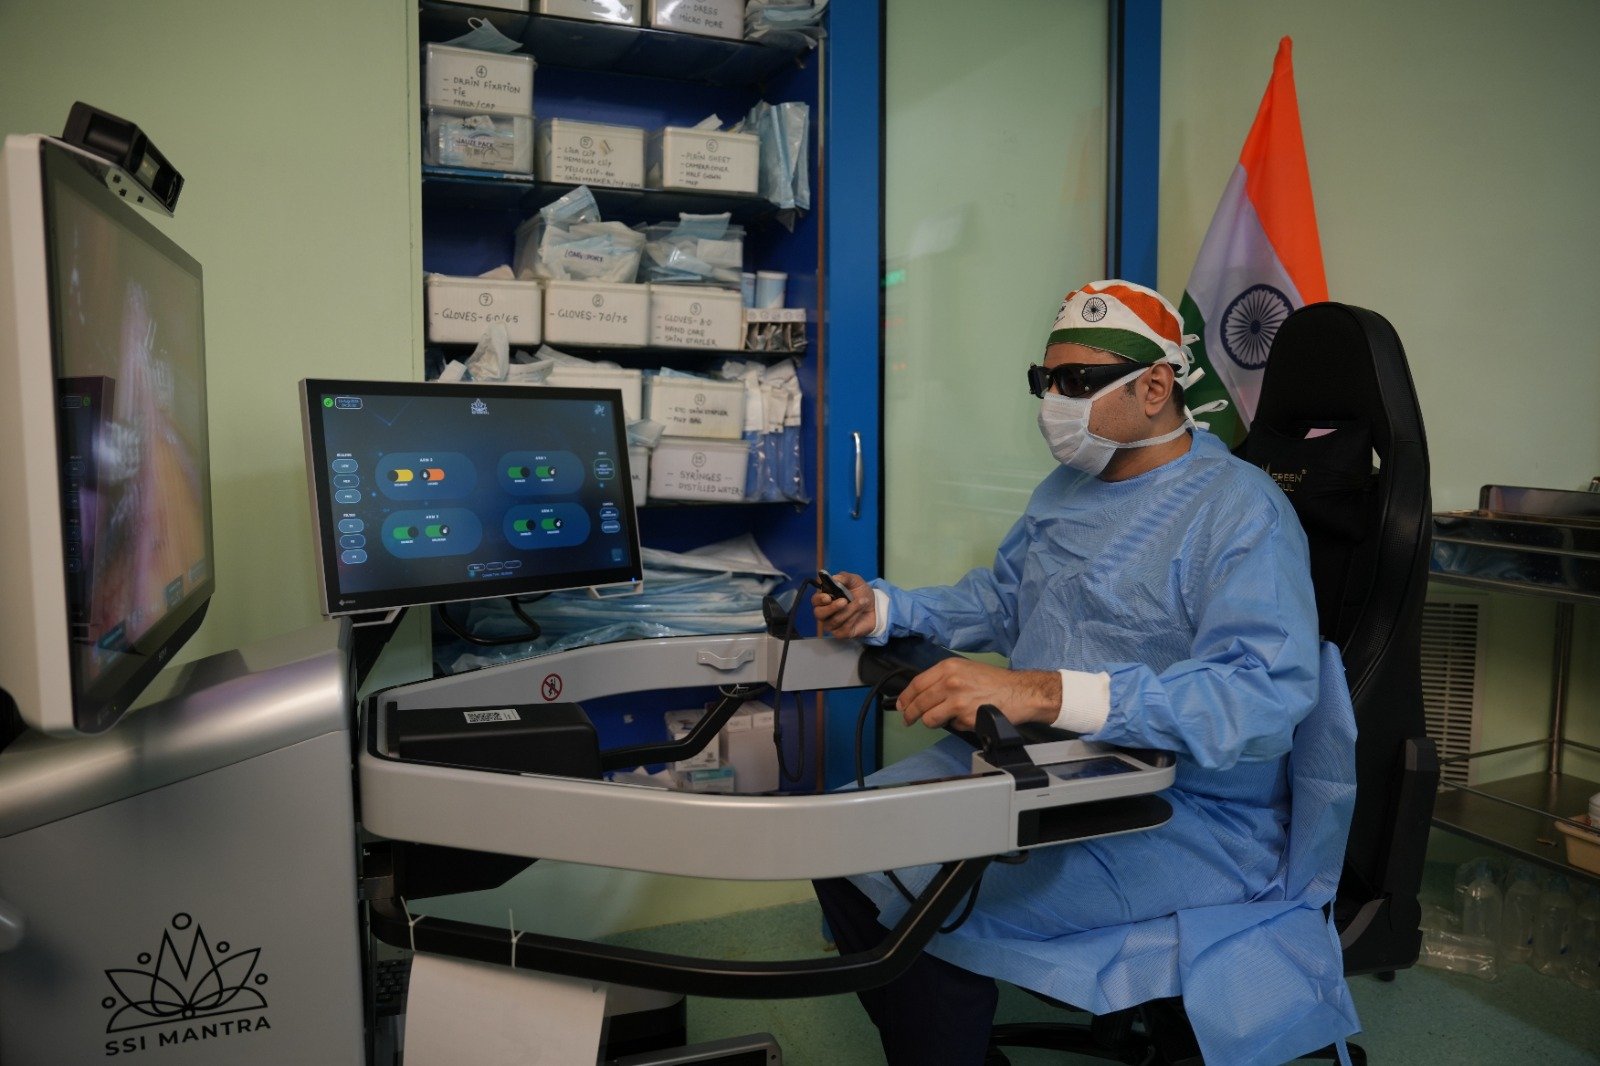

The person behind the BMI
A BMI can help classify weight. It cannot describe years of dieting, interrupted sleep, concern about diabetes, discomfort while walking, previous treatment attempts, family conversations or the hesitation before seeking professional help.
Responsible obesity communication should therefore avoid shame and sensationalism. The purpose is not to turn body size into a spectacle. It is to understand when weight may be affecting health and what medically appropriate options can be discussed.
Good obesity care should make room for both science and dignity.
The future may not belong to one diet, one medicine, one device or one operation.
It is more likely to involve better-defined treatment pathways: lifestyle and structured medical support where appropriate, medicine for some people, non-surgical interventions for others, and bariatric or metabolic surgery for patients meeting relevant clinical criteria.
The significance of that shift is larger than the arrival of any single technology.
It moves the conversation away from: “Why can't you just lose weight?”
And toward: “What is affecting your health, what have you already tried, and which next step makes clinical sense?”
That is a considerably better place to begin.
Your weight story may need a medical conversation.
If repeated attempts at weight management have not provided sustained control, or if weight exists alongside diabetes, fatty liver, sleep concerns, reduced mobility or other health problems, clinical assessment can help clarify which treatment pathways may be relevant.
Before choosing a pathway
Does everyone with obesity need bariatric surgery?
No. Treatment depends on the individual's clinical situation, including BMI, medical history, obesity-associated conditions, previous weight-management attempts and other relevant factors. Medical, non-surgical or surgical pathways may be discussed following evaluation.
Is a swallowable balloon the same as bariatric surgery?
No. A swallowable balloon is a non-surgical weight-management intervention, while bariatric surgery is a surgical treatment considered for patients meeting appropriate clinical criteria. Their indications, follow-up requirements and expected outcomes differ.
Does a robot perform robotic bariatric surgery automatically?
No. Robotic surgical systems are controlled by the operating surgeon. The technology may support visualisation, instrument movement, ergonomics and operative execution, while clinical and surgical decision-making remain with the surgeon and treating team.
Can medicines be used for weight management?
Medicine-assisted weight management may be considered for appropriate patients following medical evaluation. Choice of medication, contraindications, monitoring and follow-up should be managed by the treating clinician.
What if diet and exercise have repeatedly failed?
Repeated weight regain can be a reasonable reason to seek professional assessment. A clinician can review weight history, BMI, associated health conditions, previous treatment attempts and metabolic health before discussing appropriate next steps.
Lifestyle photographs in this article are representative imagery. Individuals shown should not be interpreted as patients of Mohak Bariatrics & Robotics unless specifically identified as such.